


Direct restoration of 1.4 and 1.5: a clinical case
Allegra Comba
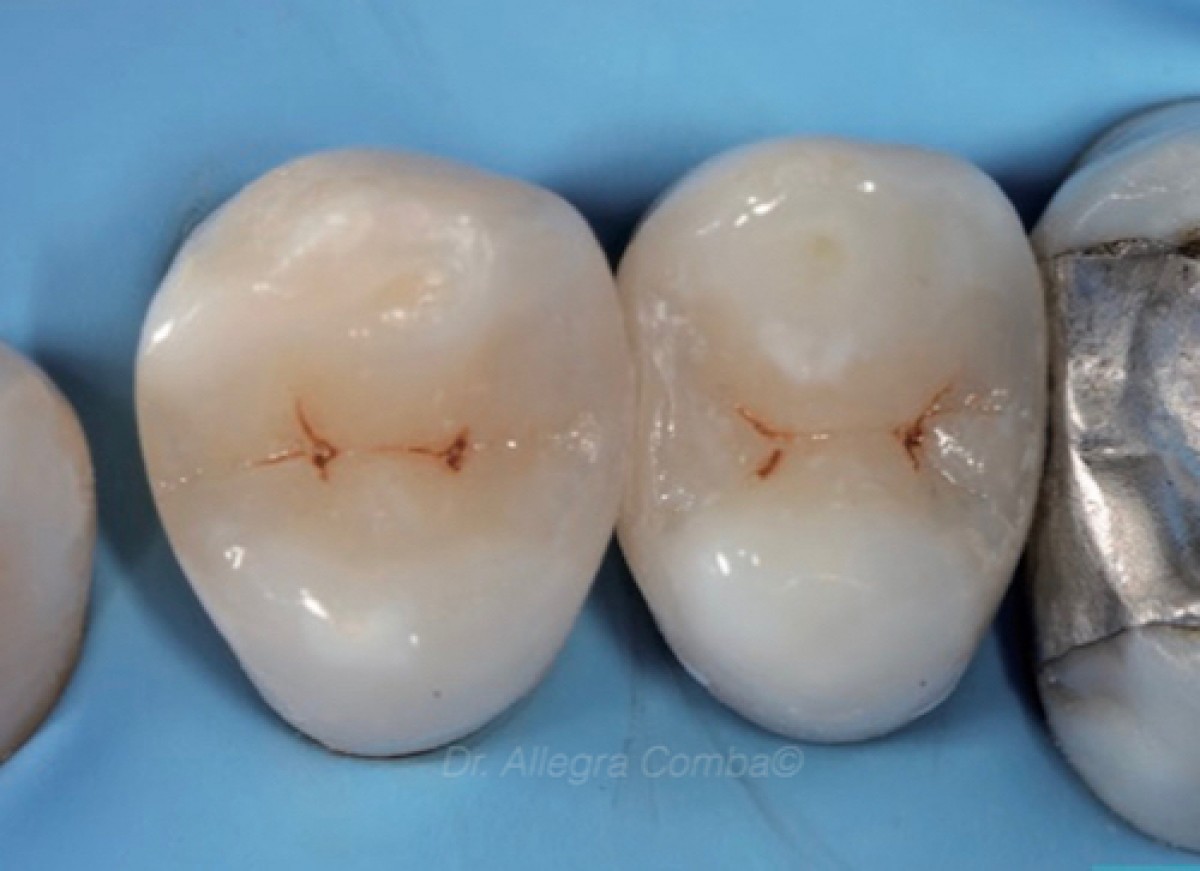
38-year-old male patient with negative medical history, who comes for a visit many years after the last dental check-up. He reports difficulty in removing food residues in the interproximal areas, in correspondence with some fractured amalgam restorations. However, it does not report pain / thermal sensitivity on any of the dental elements.
Physical and radiographic examination of the dental surfaces shows the presence of secondary carious lesions affecting the following dental elements: 1.7, 1.6, 1.5, 1.4. (Fig. 1-2)
The cold test performed on vital dental elements is positive and highlights the absence of irreversible pulp pathologies. Diagnosis Occlusal-distal carious lesion on 1.4 and mesio-occlusal-distal carious lesions on 1.5, 1.6 and 1.7.
Proposed treatment plan
Periodontal probing, scaling and root planing to remove subgingival tartar deposits;
Oral hygiene education and motivation;
Revaluation survey before proceeding with conservative therapies;
Execution of direct composite restorations on 1.4 and 1.5 and indirect restorations on 1.6 and 1.7.
We decided, for this first phase of the clinical case, to illustrate only the step-by-step clinical procedures of the direct restorations of 1.4 and 1.5. For indirect ones, we will refer to the future issue number.
STEP-BY-STEP CLINICAL PROCEDURES
1)Removal of carious lesions on 1.4 and 1.5
Isolation of the operating field with the rubber dam fixed at the level of element 1.7 with a previously sandblasted 27N hook (Fig. 3b). Subsequently, removal of the carious lesions on 14 and 15.
For the removal of the amalgams, a multi-blade tungsten drill mounted on a red ring contra-angle was used initially, under abundant jet of water and suction, followed by a cutter cylindrical diamond bur and a ceramic rosette for the removal of infected tissue at the dentin substrate level.
The cavity margins were finished with red and yellow ring diamond cutters.
The cervical steps of the cavities were also terminated with red and yellow grit diamond cutters mounted on the EVA handpiece and abrasive diamond strips.
2)Direct reconstructions on 1.4 and 1.5
Once the cleaning and finishing procedures were completed (Fig 4a), the sectional metal matrices were positioned at the level of the interproximal areas with the aid of a wooden wedge and a metal ring (Fig. 4b).
The matrices and wedges were intentionally positioned both at the level of 14 and at the level of 15 for a better distribution of the space between the restorations and to avoid a wall too pronounced in the distal direction.
After positioning the matrix system, 37% orthophosphoric acid based etching was applied on the enamel margins (30 '') and on the dentinal surfaces (15 '') of 1.4 . The etching agent was rinsed with abundant water jet for about 40 '. A 3-step etch-and-rinse adhesive polymerized 20 seconds was applied to the cleaned and dried cavities before proceeding with the reconstruction of the interproximal composite walls (Fig. 5a).
Once both proximal walls were reconstructed, a first layer (about 0.5 mm) of flowable composite, color A3, was applied to the bottom of the cavity followed by a layering of nanohybrid composite (dentin) to form a class I cavity. , color A3 (Fig. 5b).
A very thin layer of super white color was positioned at the level of the triangular crests under the final enamel layer. To complete the restoration, the brown color was applied to the furrows.
Once the first direct restoration was finished, we proceeded, as already described to the restoration on 1.5 (Fig. 6).
To finish the surfaces of both restored elements, diamond cutters with low granulometry were used, followed by paper disks with different degrees of abrasiveness, by rubber pads and brushes. The interproximal area was further refined with low-grain diamond burs mounted on the EVA handpiece and with low-abrasive metal strips, in order to maintain a correct contact point and an adequate emergence profile.
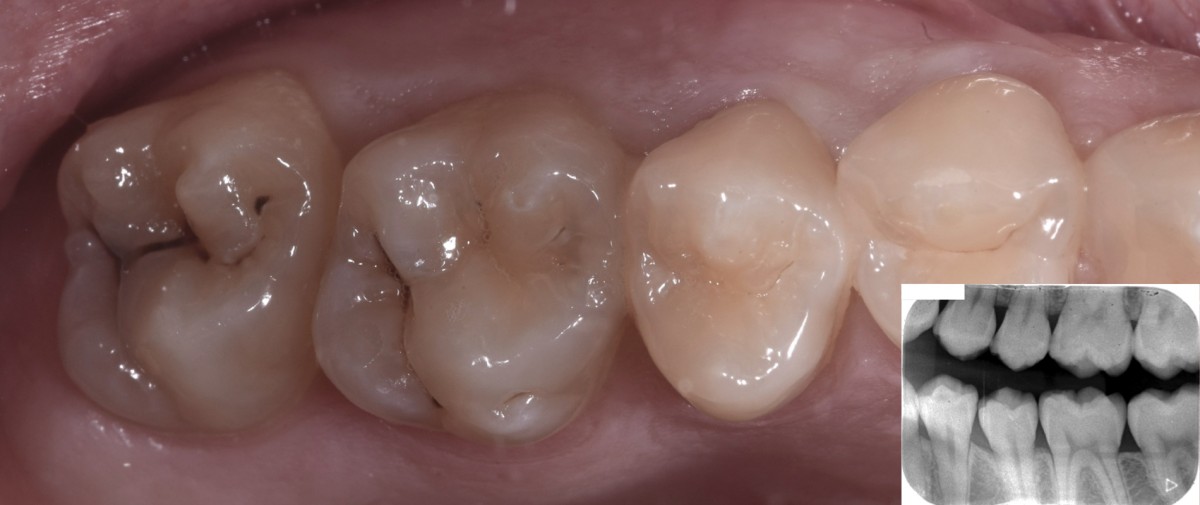
Fig 1: initial bite-wing
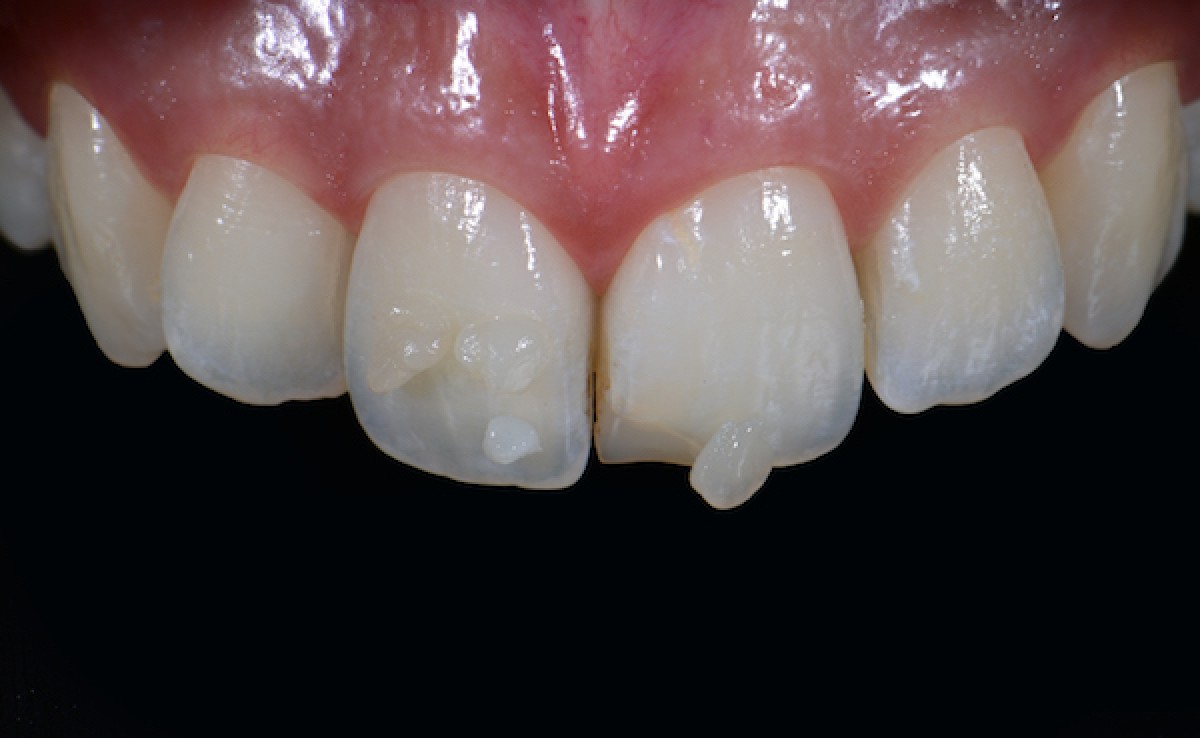
Fig 2: initial case 1.4 and 1.5

Fig 3a-b: pre- and post- isolation with dental dam

Fig 4a: Finished cavities 1.4 and 1.5; Fig 4b: sectional matrix positioning

Fig 5a: interproximal walls reconstruction; Fig 5b: composite stratification

Fig 6: final restoration 1.4 and 1.5
 Related articles
Editorials 27 September 2026
Dentistry33 survey highlights replacement care, deep caries and evolving restorative workflows
Reader survey finds direct composites remain dominant, secondary caries is the leading reason for restoration replacement, and clinicians want more training in pulp preservation
Reader survey finds direct composites remain dominant, secondary caries is the leading reason for restoration replacement, and clinicians want more training in pulp preservation
Restorative dentistry 17 April 2026
Patient Perceptions of New Robotic Technologies in Clinical Restorative Dentistry
Patient perception research has failed to focus on burgeoning technology within the dental field.
Prosthodontics 16 April 2026
The use of orthodontics before fixed prosthodontics in restorative dentistry
For a variety of reasons, orthodontic intervention is often overlooked as a viable modality to correct occlusal, axial, rotational, and space discrepancies before undertaking fixed prosthetic...
Digital Dentistry 16 February 2026
An original procedure for the ovoid pontic technique in ortho-restorative cases

In the multidisciplinary treatments, especially in case of missing teeth in aesthetic area, the compliance of patient during retention time post orthodontic therapy is evidently very high, even among...
Read more
Europe 27 September 2026 - 30 November -0001
Digital Dentistry Society Global Congress 2026: Event Preview and Professional Highlights

The Digital Dentistry Society Global Congress 2026 will take place from October 22, 2026 to October 24, 2026 in TBD, Rotating Europe, offering dental professionals a focused environment for...
Editorials 27 September 2026
Dentistry33 survey highlights replacement care, deep caries and evolving restorative workflows
Reader survey finds direct composites remain dominant, secondary caries is the leading reason for restoration replacement, and clinicians want more training in pulp preservation
Reader survey finds direct composites remain dominant, secondary caries is the leading reason for restoration replacement, and clinicians want more training in pulp preservation
Edra Professional Books 26 September 2026
Manual of oral surgery: A Practical Reference for Dental Professionals
Manual of oral surgery is an Edra professional dentistry reference focused on clinical practice, education and treatment planning.
Products 25 September 2026
Shofu Dental’s line of dental restorative materials now includes FX-LC, a next-generation, light-cure, resin-reinforced glass ionomer formulated to deliver high strength, efficient 4
News 25 September 2026

The scholarships are part of an ongoing workforce solutions strategy to help address the need for skilled dental hygienists



Copyright © 2026 - All Rights Reserved
ISSN 2767-1178